
All case studies
Case Study · Kaiser Permanente
Turning Around a Stalled Diabetes Management Pilot
A vendor-built diabetes pilot had stalled. Instead of patching it, I used patient evidence to make the harder call — rebuild a smaller, higher-value MVP — and treatment adherence rose 20%+.

Role
Director, Mobile Design & UX
Initiative
Condition Management Mobile Experience - Diabetes Pilot Redesign
Scope
Turnaround of a stalled diabetes-management product
Organization
Cross-functional Product, Design, Engineering, and Clinical partners
Geography
North America
The 15-second version
The story at a glance
20%+
Improvement in treatment adherence among app participants
<1 yr
From taking over a stalled pilot to launching the redesign
7
Disciplines in one product team — from patients to a clinical psychologist
01 The situation
A vendor-built diabetes management pilot had stalled, with low engagement, high abandonment, low CSAT, and weak adherence to recommended treatment.
02 My move
I took ownership, established a baseline, spoke directly with patients, and reframed the choice from patching the existing app to rebuilding a smaller, higher-value MVP.
03 The outcome
The redesigned pilot launched later that year, increasing engagement and CSAT, reducing abandonment, and improving treatment adherence by 20%+ among app participants.
The pivotal decision
Rather than spend more time and resources retrofitting a low-performing vendor product, I recommended preserving the useful learning, reducing the scope, and rebuilding a focused MVP around the highest-value patient and clinical needs.
The full story
For those who want the detail
Chapter 01
The challenge
Kaiser Permanente had commissioned a vendor to build a pilot mobile application for diabetes condition management. The intent was strong, but the experience was not producing the behavior or satisfaction the program needed. Engagement had stalled, abandonment was high, CSAT was low, and adherence to clinically recommended treatment remained weak.
When I took over the initiative, the question was not simply how to improve screens. We needed to determine whether the existing product was worth continuing to invest in, what patients actually needed from the experience, and how to improve both the user experience and the clinical outcome without allowing sunk cost to drive the decision.
Chapter 02
My mandate
My responsibility was to stabilize the initiative, create an evidence-based path forward, align leadership around the tradeoff, and give the team a product model that could deliver measurable patient value within the year.
The team model
A close cross-functional team brought together UX design, research, clinicians, patients, Engineering, Product, and a clinical psychologist using an SVPG-inspired product operating model.
Chapter 03
How I approached it
01
Put patients into the decision process
I spoke directly with end users to understand where the experience created friction, where people disengaged, and which parts of condition management felt most difficult to sustain. Those conversations helped us separate feature requests from the underlying problems patients needed the product to solve.
02
Reframe the investment decision
The evaluation showed that retrofitting the existing application would require more time and resources than rebuilding a smaller product around the core value proposition. I brought that tradeoff to stakeholders and leadership and secured alignment to move forward with a scaled-down MVP rather than continue patching the existing pilot.
03
Build a genuinely multidisciplinary product team
We used the Silicon Valley Product Group (SVPG) operating model as a guide and formed a close working team across UX design, research, clinicians, patients, Engineering, Product, and a clinical psychologist. The point was not simply representation. It was to keep product, clinical, technical, behavioral, and patient perspectives in the same decision loop from discovery through delivery.
04
Design for value first, then scale
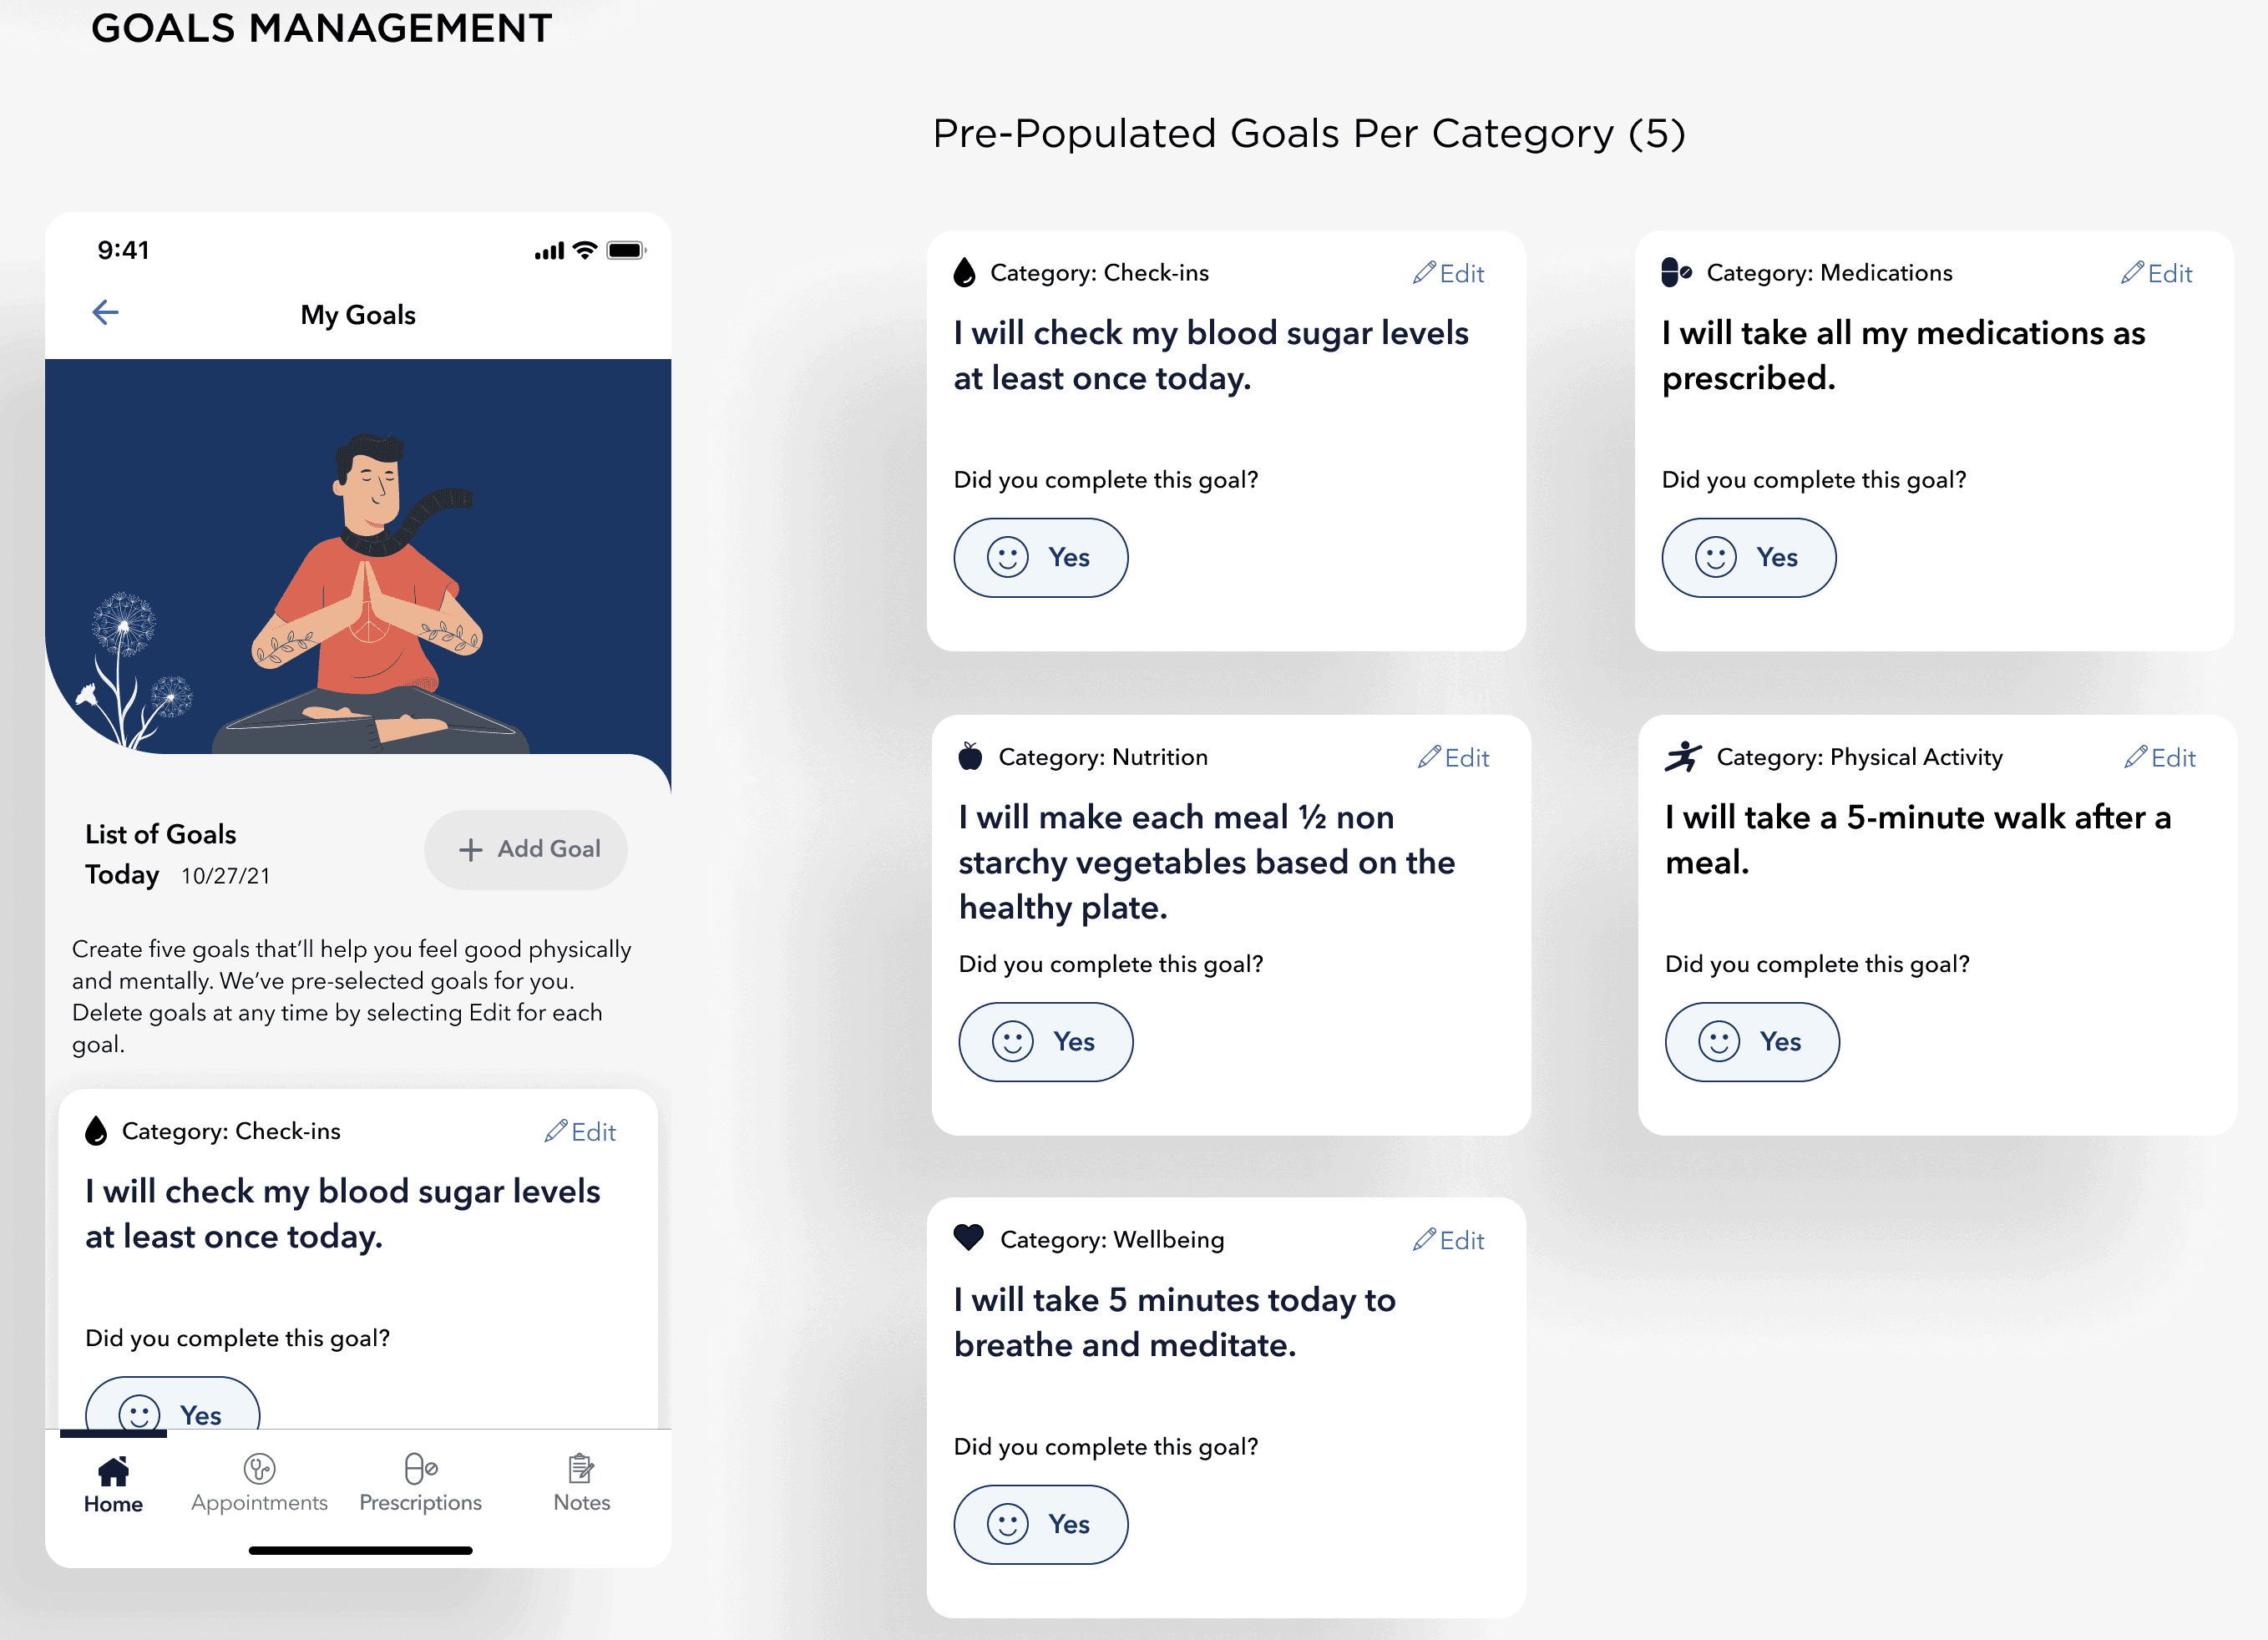
The team worked together to scope, design, and build the MVP around the highest-value interactions. We deliberately kept the first release focused instead of recreating the full feature set. At the same time, we designed the product so the approach could become a template for additional condition-management experiences rather than a one-off diabetes solution.
05
Launch and measure against the same baseline
The redesigned pilot was released later that same year. After launch, we returned to the same categories we had baselined at the start so the team and leadership could assess whether the new product was actually changing behavior and satisfaction.
Chapter 04
Results
We re-sampled the same categories used in the baseline so the team could compare the new experience against the original state.
Engagement
Stalled / Low
Higher engagement after the redesigned pilot launched
Abandonment
High
Lower abandonment
CSAT
Low
Higher customer satisfaction
Treatment adherence
Low
20%+ increase among app participants
Scalability
Single vendor-built pilot
Designed as a reusable template for additional condition-management experiences
Chapter 05
Why it worked
Evidence before solutioning
We did not start with a redesign concept. We first established the baseline and used patient input to define the actual sources of friction.
A smaller product with a clearer job to do
Reducing scope gave the team room to concentrate on value instead of preserving every feature in the existing application.
Patients and clinicians inside the product loop
Continuous input from end users and clinical partners helped the team validate both usability and clinical relevance.
A decision model leadership could support
Framing the choice as a resource and value tradeoff made it easier to move beyond sunk cost and align around a focused rebuild.
Chapter 06
What I learned
End users need to be involved from beginning to end, not brought in only to validate a nearly finished solution.
There are times when the fastest responsible move is to keep the learning, stop patching the existing product, and start over with a clearer scope.
A smaller MVP that solves the most important problems well can create more value than a feature-heavy product that users abandon.
Chapter 07
The system, visualized


Leadership takeaway
The turnaround was not driven by adding more features. It came from using evidence to make a harder portfolio decision, narrowing the product to its highest-value purpose, and keeping patients, clinicians, design, product, and engineering tightly connected through delivery.